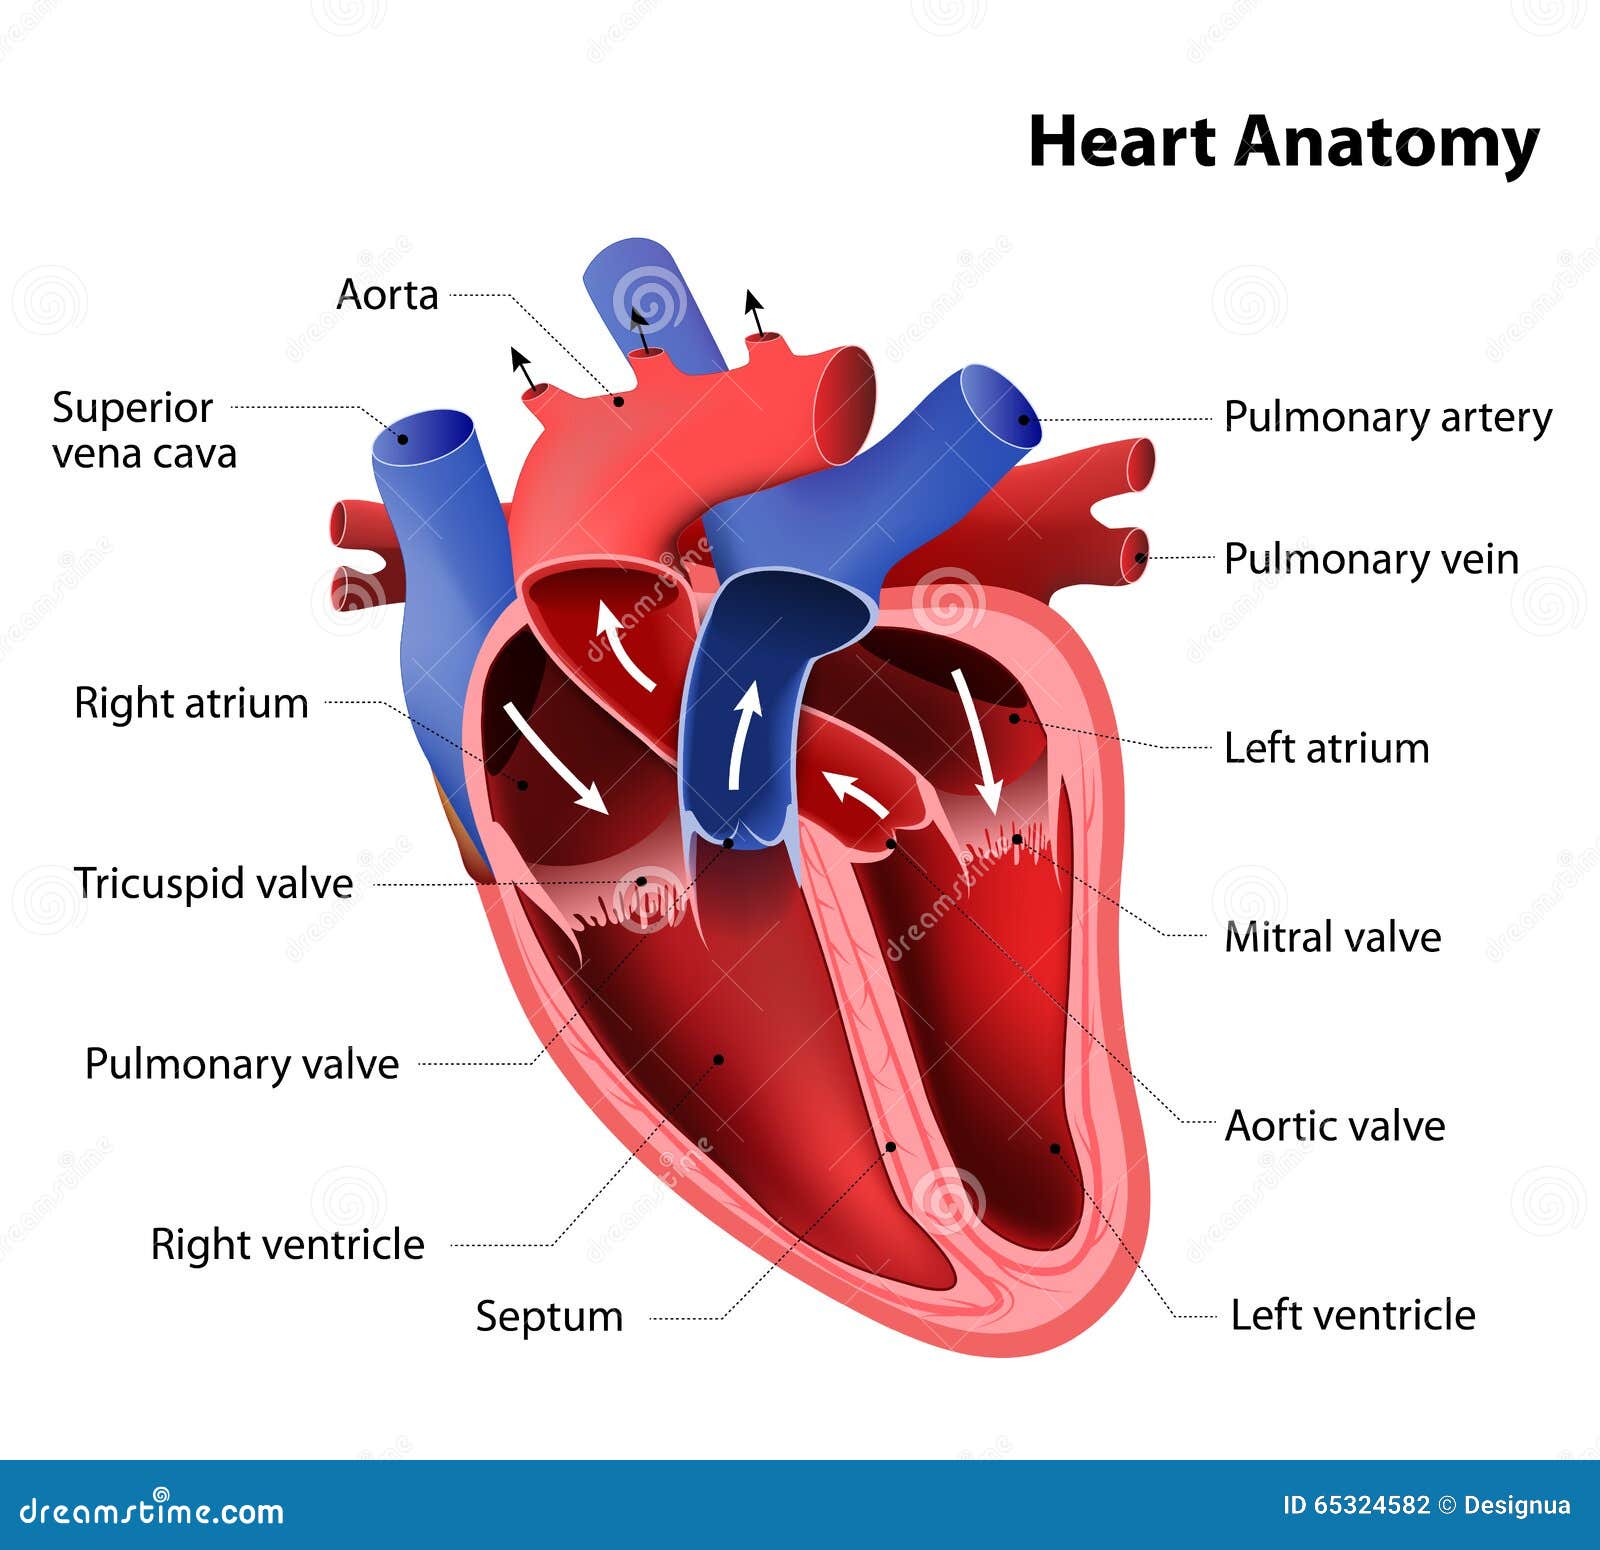
When doctors listen to your chest with a stethoscope, they are tuned in to the rhythmic closing of your heart valves. You know this cadence as the familiar lub-dub. But beneath those prominent heart sounds lies a complex acoustic spectrum that clinicians have spent decades evaluating. The term cardiac rrr refers to specific acoustic phenomena and rhythm markers in the cardiac cycle, particularly involving the third heart sound, or S3, which signals how blood flows into the ventricles during diastole.
For years, clinicians relied on subjective auscultation to catch these subtle frequencies. Today, modern acoustic sensors and advanced signal processing allow medical professionals to measure these vibrations with precision. This shift from manual listening to quantitative acoustic analysis is changing how specialists evaluate ventricular compliance, monitor heart failure, and detect early signs of cardiovascular distress long before outward symptoms appear.
The Physiology Behind the Sounds
Your heart doesn't just open and close valves; it creates a symphony of vibrations driven by blood movement, muscular contraction, and wall tension. The standard first heart sound (S1) marks the closure of the mitral and tricuspid valves, while the second sound (S2) marks the closure of the aortic and pulmonic valves.
The cardiac rrr dynamics often center around the diastolic phase—specifically the rapid filling period. When blood rushes from the atria into a relatively stiff or overfilled ventricle, it creates a low-frequency vibration.
- First Heart Sound (S1): Initiation of systole, closure of atrioventricular valves.
- Second Heart Sound (S2): End of systole, closure of semilunar valves.
- Third Heart Sound (S3): Early passive ventricular filling, often linked to the acoustic profile of the cardiac rrr.
- Fourth Heart Sound (S4): Late active filling driven by atrial contraction against a stiff ventricular wall.
Understanding these intervals requires recognizing that a healthy heart relaxes smoothly. When ventricular compliance drops, the acoustic signature shifts. Modern diagnostic equipment captures these subtle shifts, giving physicians a non-invasive look at internal pressures. You can learn more about clinical evaluations and heart assessments through resources provided by the American Heart Association.
From Subjective Auscultation to Quantitative Acoustics
Historically, detecting extra heart sounds depended entirely on the physician's hearing acuity and the quality of their acoustic stethoscope. Faint or low-frequency rrr patterns were easily missed, especially in noisy clinical environments or in patients with higher body mass indexes.
Advanced digital stethoscopes and phonocardiography have transformed this diagnostic step. By converting acoustic waves into visual phonocardiograms and filtering out ambient noise, technology isolates specific frequencies. Clinicians can now measure:
- Amplitude: The loudness or intensity of the vibration relative to baseline sounds.
- Timing: The exact millisecond the acoustic event occurs during the cardiac cycle.
- Frequency Spectrum: The tonal distribution, helping differentiate benign murmurs from pathological signals.
This objective data removes guesswork. Instead of noting a vague extra sound, a cardiologist can track numerical changes in acoustic output over successive check-ups.
Clinical Implications in Heart Failure and Ventricular Compliance
The primary value of monitoring the cardiac rrr lies in detecting diastolic dysfunction and heart failure with preserved ejection fraction (HFpEF). In HFpEF, the heart muscle becomes stiff, preventing adequate filling even though the pumping action remains strong.
Traditional tests like standard blood panels or basic physical exams might not catch early-stage stiffness. However, an emerging or intensifying rrr acoustic marker often correlates with elevated left ventricular end-diastolic pressure.
- Early Triage: Detecting unexpected acoustic changes during routine visits prompts timely echocardiograms.
- Therapeutic Monitoring: Tracking whether prescribed medications successfully improve ventricular relaxation over weeks and months.
- Risk Stratification: Identifying patients at higher risk for sudden fluid overload or acute decompensation.
For comprehensive guidelines on managing heart failure symptoms and diagnostic benchmarks, check the National Institutes of Health.
Practical Applications in Modern Care Pathways
The integration of advanced acoustic tools reshapes patient management across multiple healthcare settings. By catching mechanical inefficiencies early, care teams intervene before patients experience severe shortness of breath or emergency hospitalization.
Emergency and Acute Care
In fast-paced environments, clinicians need rapid assessment tools. A newly amplified cardiac rrr in a patient presenting with mild peripheral edema serves as an immediate red flag, signaling that the heart is struggling to handle fluid loads and prompting immediate imaging.
Chronic Disease Management
Patients managing hypertension, diabetes, or early-stage renal disease face elevated risks of developing structural heart changes. Regular acoustic monitoring acts as an early warning system, allowing physicians to adjust dosages or recommend lifestyle changes before permanent tissue remodeling occurs.
Post-Operative Recovery
Following cardiac procedures, surgical teams monitor recovery trajectories closely. Tracking the evolution of heart sounds provides real-time feedback on how the myocardium responds to surgical repair and reperfusion.
Common Misconceptions About Extra Heart Sounds
Misunderstandings around heart sounds often lead to unnecessary anxiety or overlooked conditions. Clarifying these points helps patients and medical students alike interpret diagnostic data accurately.
- Misconception: Every extra sound indicates heart failure.
- Reality: Younger individuals and athletes often present with a physiological S3 sound that is entirely benign and normal.
- Misconception: Stethoscopes are obsolete compared to imaging.
- Reality: While echocardiograms provide definitive structural views, acoustic sensors offer continuous, low-cost monitoring that guides when imaging is necessary.
- Misconception: Heart sounds remain constant throughout the day.
- Reality: Hydration status, posture, and physical exertion temporarily alter acoustic profiles, requiring standardized measurement protocols.
Frequently Asked Questions
What causes a cardiac rrr sound to occur?
It is typically generated by the rapid deceleration of blood entering the ventricle during early diastole, creating vibrations against the ventricular walls when compliance is altered.
Is an extra heart sound always dangerous?
No. In children, teenagers, and pregnant individuals, a third heart sound is often normal. Pathological significance depends on age, medical history, and accompanying symptoms.
How do digital stethoscopes improve detection?
Digital stethoscopes amplify sound frequencies human ears miss and filter out ambient room noise, allowing clinicians to record and analyze acoustic waveforms digitally.
Can wearable devices monitor heart sounds?
While traditional smartwatches primarily track electrical signals via ECG or pulse via photoplethysmography, emerging research explores acoustic sensors capable of capturing subtle vibrations directly from the chest wall.